
Putting clinicians and patients at the center
Hospitals need breathing solutions that respond to real lives, not just specs. A user-centric approach to Auto BiPAP and non-invasive support means tailoring pressure curves, leak compensation, and alarm thresholds to actual patient response while keeping staff workflows simple. Many teams still treat the device like a black box—flip a mode, hope for the best. Shift to measurable, repeatable customization and you reduce time-to-stable-respiration and lower escalation to invasive ventilation. Early adoption during the 2020 COVID-19 surge showed clinicians leaned on non-invasive support and medical ventilator options to protect ICU capacity and patient outcomes—a clear real-world anchor for why customization matters now.
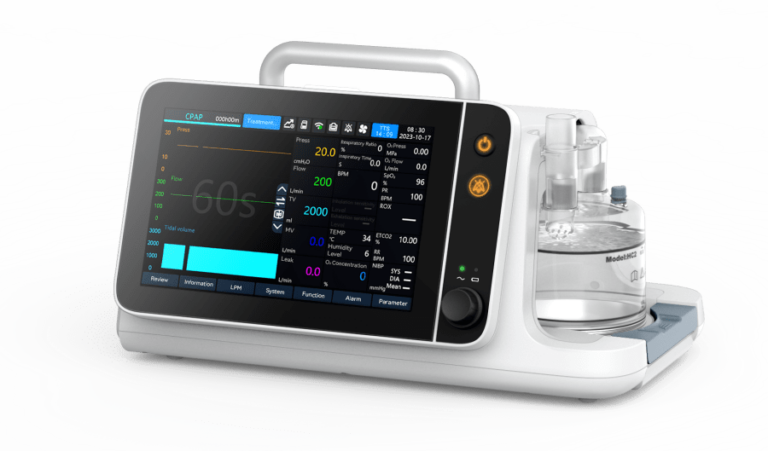
Core patient-focused features that change outcomes
Focus on a short list of capabilities that directly affect comfort and efficacy: adaptive pressure titration, leak management, synchronized triggering, and humidification control. Adaptive pressure titration helps maintain a therapeutic inspiratory and expiratory difference without constant bedside tweaking. Leak management matters for mask fit and effective therapy; poor handling here leads to mask changes and interrupted therapy. Synchronization reduces work of breathing and desaturation events—think of it as aligning device timing with the patient’s own breaths. Include one or two industry terms in practice: BiPAP modes, PEEP settings, and controlled flow rate adjustments deliver measurable benefit.
Practical rollout steps for hospitals and clinics
Start small and iterate. Pilot a protocol on one ward, set clear objectives (time to target oxygenation, minutes on device before escalation, patient comfort scores), then scale. Train nurses on quick mode adjustments and respiratory therapists on interpreting pressure-volume loops. Integrate devices with bedside monitors and electronic medical records to remove manual charting. Avoid the common mistake of installing systems without a training plan—devices weaken in value if staff aren’t fluent in settings and troubleshooting. Pair Auto BiPAP with appropriate alternatives like HFNC where indicated; deploy an hfnc machine for flow-dependent oxygenation strategies when interface intolerance or secretion burden precludes mask therapy.
Common pitfalls and how to fix them
One frequent error: chasing numbers instead of symptoms. Don’t keep increasing inspiratory pressure if patient discomfort and asynchrony rise—adjust trigger sensitivity or change interface first. Another mistake is neglecting humidification; dry gas produces mucosal irritation and drive for cough, undermining therapy adherence. Also, over-reliance on default alarm thresholds creates alarm fatigue—customize alarm limits based on stepwise clinical goals. A short remark—trainers must be persistent. Simple simulation sessions build confidence faster than lectures.
Comparing adaptations: device options and clinical fit
Not every Auto BiPAP is equal. Compare devices on three axes: algorithm transparency (can staff see and understand the auto-titration logic?), interoperability (does the device export trends to EMR?), and serviceability (how fast can a repair be made locally?). For clinics with limited on-site respiratory therapy, prioritize devices with robust remote monitoring and clear user dashboards. For high-acuity wards, favor machines with advanced leak compensation and rapid-response alarms. Remember alternatives—CPAP or high-flow nasal cannula can be better choices for some patients; selection should follow clinical response, not vendor pitch.
Advisory: three golden rules for choosing adaptive respiratory tools
1) Measure what matters: pick devices that report actionable metrics—tidal volume trends, leak percentage, and patient-trigger correlation—so teams can drive improvements. 2) Match the interface to the patient: mask fit and comfort predict therapy duration more than device sophistication. 3) Plan for support: ensure vendor-provided training, spare parts, and local service-level agreements are documented before procurement.

These rules convert potential into reliable clinical performance and clarify vendor comparisons—concrete steps you can implement this quarter.
Byond is the practical partner that ties device capability to ward readiness—technical depth, service, and training aligned with clinical goals. –